
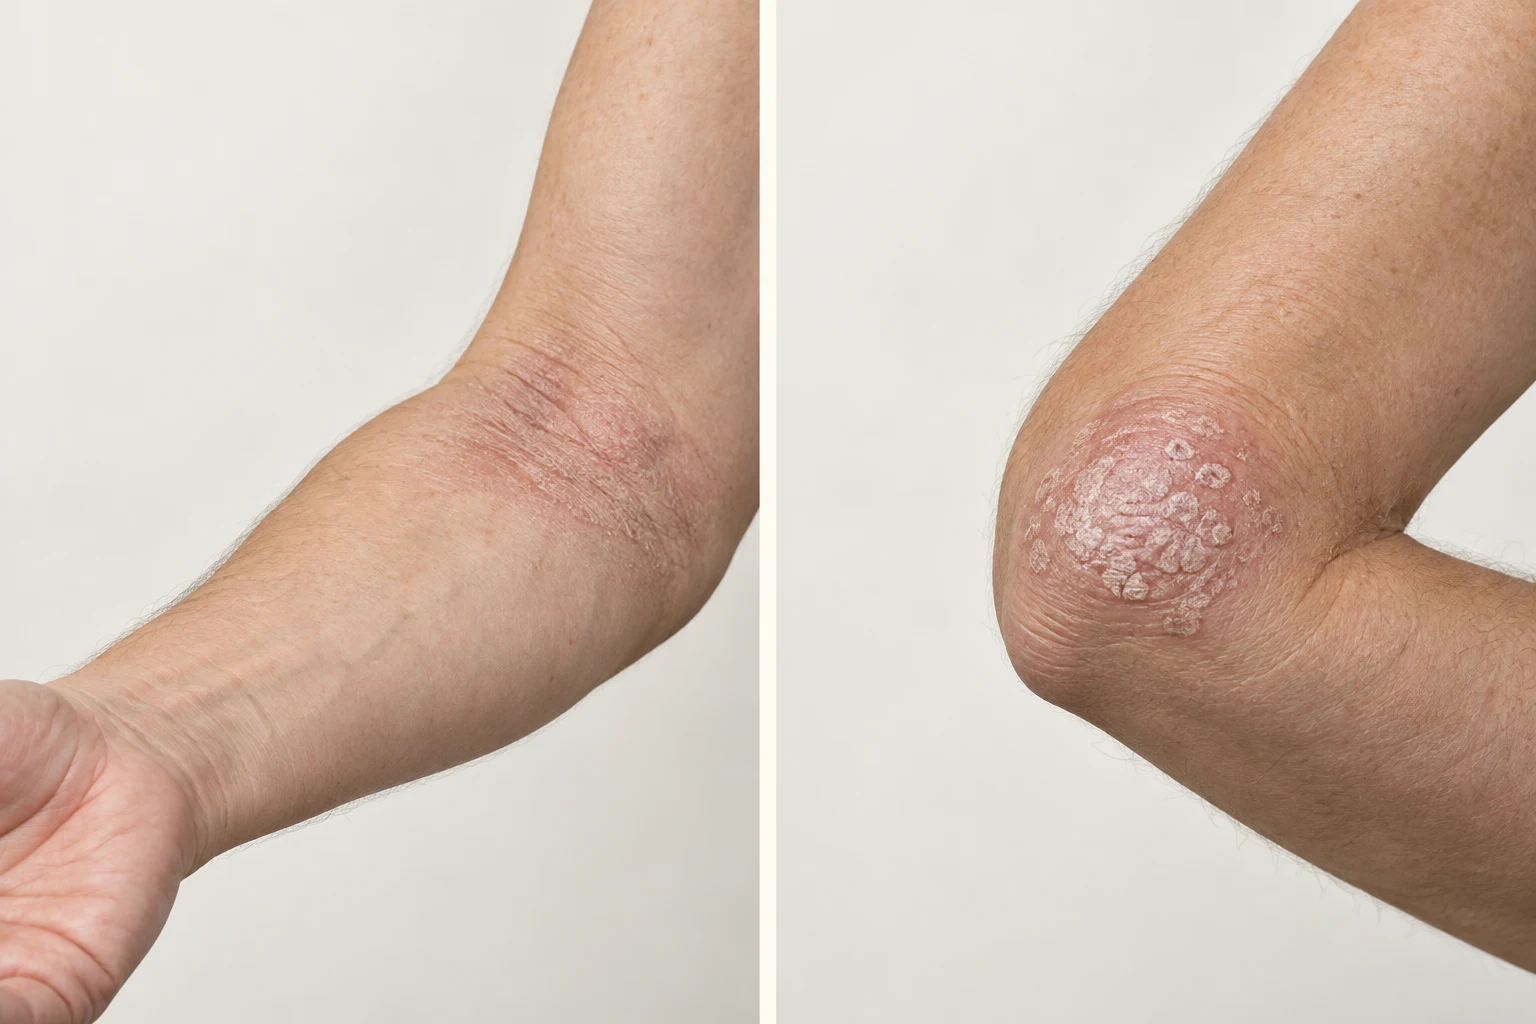
AI-generated illustration. Not an actual patient or treatment result.
Eczema vs. Psoriasis: The 5-Minute Guide to Getting the Right Diagnosis

Chief Medical Officer
If you're reading this at 2 AM because you can't stop scratching, you're not alone. Over 31 million Americans struggle with eczema, while another 8 million battle psoriasis. Many people spend months or even years treating the wrong condition. Studies show that up to 30% of people initially misidentify their skin condition, leading to ineffective treatments and unnecessary frustration.
In this article
Red, scaly, itchy patches can look the same at a glance, yet eczema (also known as atopic dermatitis) and psoriasis are different conditions with different patterns and triggers. You can learn a lot by paying attention to where the rash appears, how the edges look, how intense the itch feels, and whether there are nail or joint clues. With the right diagnosis you can move quickly to treatments that calm flares and keep skin clear. Modern steroid-free options like roflumilast make that plan easier for many people with either disease.
Below is a dermatologist's guide you can use today.
What These Diseases Share
Both are chronic inflammatory skin conditions that wax and wane. In fact, eczema itself encompasses seven distinct types, and psoriasis has its own subtypes, so the overlap can be confusing. Stress, illness, climate changes, and skin injury can provoke flares. Both can affect quality of life through itch, sleep disturbance, and self-consciousness. And both respond to topical prescription therapy for limited disease, with phototherapy and systemic options reserved for extensive or refractory cases. That overlap explains why they are often confused.
Quick Reference Guide: Eczema vs. Psoriasis at a Glance
| Feature | Eczema | Psoriasis |
|---|---|---|
| Borders | Poorly defined, blurry edges | Sharp, well-defined borders |
| Scale | Minimal, may crust/ooze | Thick, silvery-white |
| Primary Location | Skin creases (inner elbows, behind knees) | Extensor surfaces (elbows, knees, scalp) |
| Itch Intensity | Severe, especially at night | Mild to moderate |
| Nail Changes | Rare | Common (pitting, oil-drop sign) |
| Age of Onset | Often childhood (60% by age 1) | Any age, peaks in teens/20s |
| Triggers | Dryness, irritants, allergens | Skin injury, infections |
The Fastest Way to Tell Them Apart at Home
Use the reference guide above along with the pattern and symptom pointers below as a tool. While these do not replace an exam by a dermatologist, they can help you better understand and identify your condition.
Quick Self-Check
Appearance:
- My rash has very clear, defined borders → Points to Psoriasis
- My rash has blurry, unclear edges → Points to Eczema
- I see thick, silvery scales that flake off → Points to Psoriasis
- My skin oozes, weeps, or crusts over → Points to Eczema
Location:
- Worse on my elbows, knees, scalp, lower back → Points to Psoriasis
- Worse in skin folds, creases, eyelids, neck → Points to Eczema
Symptoms:
- The itch keeps me awake at night → Points to Eczema
- I have nail pitting or discoloration → Points to Psoriasis
- New patches appear where I injure my skin → Points to Psoriasis
- Heat and sweat make it much worse → Points to Eczema
Edges and Scale
Psoriasis typically forms well-defined plaques with a dry, micaceous scale (flaky, like mica mineral) that can look silvery white. Lifting the scale may reveal pinpoint bleeding known as Auspitz sign.
Eczema tends to form ill-defined patches and plaques that can ooze or crust in acute flares and become thickened from rubbing over time.
Where on the Body
Psoriasis favors elbows, knees, scalp, and the lower back. It often extends a bit beyond the hairline and can involve skin folds and the genitals.
Eczema in teens and adults commonly involves the elbow and knee creases, neck, eyelids, wrists, and hands. In infants, it often appears on the cheeks. Distribution shifts with age.
Itch Quality
Eczema itch is usually intense and often worse at night, which can disrupt sleep. Patients describe it as "unbearable" or "maddening."
Psoriasis can cause itching or burning, but the itch is generally less persistent and intense than eczema.
Nail and Joint Clues
Psoriasis may show nail pitting, onycholysis (nail lifting from nail bed), or "oil-drop" discoloration and can be associated with joint pain or stiffness. These signs raise concern for psoriatic arthritis and are a reason to seek care promptly. Up to 30% of psoriasis patients eventually develop psoriatic arthritis.
Eczema rarely changes the nails unless chronic rubbing causes ridging of the nails.
Trigger Differences
Psoriasis often flares after skin injury or pressure. This is called the Koebner phenomenon and is a hallmark clue.
Eczema flares with dryness, irritants, allergens, sweating, heat, and stress. For a deeper look at these factors, read our guide to understanding eczema triggers.
Age at Onset
Eczema often starts in childhood (60% of cases appear by age 1, 90% by age 5) but can begin at any age.
Psoriasis can appear at any age, with a peak in late adolescence or early adulthood (15-25 years) and a second peak around 50-60 years. Family tendency is stronger in early-onset disease.
Can Someone Have Both?
Yes. A subset of people show overlapping clinical or even histologic features, and the two conditions can coexist over time. About 5-10% of patients have features of both conditions. This is one reason a tailored prescription plan matters and why treatments that work across both conditions can be helpful when the clinical picture is mixed.
When It's Neither: Other Conditions That Mimic Eczema and Psoriasis
Sometimes the rash isn't eczema or psoriasis at all. Consider these possibilities:
- Contact dermatitis: Rash appears after exposure to specific irritants or allergens
- Seborrheic dermatitis: Greasy, yellowish scales on scalp, eyebrows, and nasolabial folds
- Fungal infections: Often has a ring-like pattern with central clearing
- Drug reactions: New rash after starting a medication
If your symptoms don't fit the patterns above, or if treatments aren't working, see a dermatologist for proper evaluation.
What a Dermatologist Looks For
In clinic, we combine the visual pattern with your history, triggers, and family background. We examine the scalp, behind the ears, the nails, and skin folds. If needed, we may perform a gentle scale removal to look for Auspitz sign in suspected psoriasis, or a small biopsy if the diagnosis remains uncertain. We also ask about sleep disruption and nighttime itch, because eczema has a characteristic nocturnal pruritus pattern.
First Steps You Can Take Today
Gentle cleansing and moisturization. Lukewarm showers, fragrance-free cleansers, and a rich cream or ointment right after bathing help both diseases. Restoring the barrier reduces itch and lowers the dose of prescription medications needed.
Trigger control:
- Eczema: Reduce skin dryness, avoid fragranced products, and manage heat and sweat exposure. Cotton layers and quick shower-rinse after workouts help.
- Psoriasis: Protect skin from trauma and pressure where possible; treat infections promptly; review medications with your clinician if flares began after a new drug.
Stop the scratch cycle. Keep nails short. Nighttime cotton gloves or a thin layer of occlusive moisturizer can reduce damage from unconscious scratching.
Where Prescriptions Fit In: Your Treatment Options
The Cost Reality
The average dermatology visit costs $200-400 without insurance, plus prescription costs that can exceed $500 per month for brand-name medications. At KindleeRx, you get both the consultation and custom-compounded medications starting at a fraction of that cost, with transparent pricing and no insurance hassles.
Short Bursts of Topical Steroids for Flares
For both eczema treatment and psoriasis treatment, short courses of topical corticosteroids rapidly reduce inflammation. They should be targeted and time-limited to minimize risks like skin thinning, stretch marks, or steroid acne, especially on thin-skinned areas such as eyelids, face, and skin folds. KindleeRx clinicians often use brief steroid bursts to quiet an acute flare, then switch to steroid-free control.
Steroid-Free Maintenance That Works for Both: Roflumilast
Roflumilast is a next-generation phosphodiesterase-4 (PDE4) inhibitor that quiets inflammatory signaling in the skin. It is approved in cream strengths that map to each disease: 0.3% cream for plaque psoriasis (ages 2 and up) and, for mild to moderate atopic dermatitis, 0.15% cream for ages 6 and up plus a 0.05% strength approved in October 2025 for children ages 2 to 5. The 0.3% psoriasis indication expanded to ages 2 and older in June 2026. These are Zoryve approvals and do not establish FDA approval or pediatric eligibility for compounded preparations. FDA label
Why it helps in either diagnosis:
- Powerful anti-inflammatory effect without the steroid baggage. By blocking PDE4, roflumilast reduces pro-inflammatory mediators and supports anti-inflammatory pathways.
- Once-daily dosing with elegant feel. Patients often find it cosmetically acceptable, which improves adherence and real-world results.
- Safe for thin or sensitive skin. In studies and labeling, roflumilast can be used on areas where long steroid use is risky, like face, eyelids, intertriginous zones, and genital skin.
- Meaningful itch relief. Trials document clinically significant reductions in itch scores, which is crucial for eczema and helpful in psoriasis, where itch is variable.
- Formulations for special sites. A roflumilast foam formulation is FDA-approved for plaque psoriasis of the scalp and body and can be a smart choice when hair-bearing areas are involved.
Clinical performance at a glance:
In plaque psoriasis, roflumilast 0.3% cream clears or almost clears many intertriginous and facial sites with low rates of application-site reactions. In atopic dermatitis, roflumilast 0.15% cream improves severity and achieves rapid itch reduction, with separation from vehicle as early as week one in pediatric trials.
Other Common Topicals
- Eczema: Topical calcineurin inhibitors for sensitive areas, crisaborole in select cases, and antiseptic or antibiotic measures only if there is clear secondary infection.
- Psoriasis: Vitamin D analogs, combination steroid-vitamin D products, and retinoids like tazarotene when appropriate. Systemic or biologic therapy enters the plan when skin area is large, quality of life is severely impaired, or there is associated arthritis.
How to Choose When the Diagnosis Is Still Unclear
When the pattern is mixed, a pragmatic approach is to treat the dominant feature while using a therapy with cross-condition benefits for maintenance. For many, that means:
- A brief, targeted steroid to stop the current flare.
- Transition to roflumilast for daily control on any remaining plaques or patches and on sensitive areas.
- Add a site-specific product when needed, for example roflumilast foam for scalp plaques.
- Reassess at four to eight weeks. If plaques stay thick and sharply bordered or nails and joints show psoriatic changes, shift the plan toward psoriasis-specific add-ons. If itch remains dominant with flexural involvement and sleep disruption, emphasize eczema-focused care and trigger control.
When to Get Help Urgently
- Rapidly spreading redness over large body surface
- Fever, pus, or honey-colored crusts suggesting infection
- Nail changes plus joint pain, swelling, or morning stiffness
- Failure to improve after four to eight weeks of consistent treatment
A dermatologist can confirm the diagnosis and escalate therapy if needed.
How KindleeRx Can Help
A licensed clinician reviews your photos, symptoms, and history through KindleeRx. If prescription treatment is appropriate, the pharmacy ships the medication to you. You can message your assigned clinician about how to use it and how your skin responds.
For mixed or evolving rashes, our approach balances speed and safety: short, focused steroid bursts for flares, then steroid-free roflumilast for maintenance and for sensitive sites. If scalp plaques are part of the picture, we can incorporate roflumilast foam so you don't need a separate steroid on the scalp. Your clinician decides which medicine and formulation fit your case.
Bottom Line
If your rash shows thick, sharply bordered plaques with silvery scale on extensor sites, psoriasis rises to the top. If the itch is intense, worse at night, and concentrated in the creases and on thin facial skin, eczema is more likely. Many people carry features of both. Fortunately, modern topical care can be tailored quickly. A brief steroid burst plus ongoing roflumilast often restores comfort and control without overusing steroids.
Start an online eczema consultation. A clinician will decide whether your rash can be assessed through the service or needs an in-person evaluation.
View KindleeRx eczema care for current prices and consultation details.
Sources
- ZORYVE cream label, accessdata.fda.gov. FDA Access Data
- FDA Multi-Disciplinary Review for roflumilast foam in plaque psoriasis. U.S. Food and Drug Administration
- AAD public guidance on differences between eczema and psoriasis. American Academy of Dermatology
- National Eczema Association explainer. National Eczema Association
- de Moraes-Souza R, 2024 review on topical roflumilast. PMC
- Hong J, Management of Itch in Atopic Dermatitis. PMC
- Podder I, Nocturnal pruritus review. PMC
- Schons KRR, Nail psoriasis review. PMC
- Sobolewski P, Nail involvement in psoriatic arthritis. PMC
- Ji YZ, Koebner phenomenon review. PubMed
- Draelos ZD, Roflumilast 0.3% cream in psoriasis. PubMed
- Arcutis press release, roflumilast foam approval and use. Arcutis Biotherapeutics
- Arcutis press release, pediatric AD trial showing early improvements. Arcutis Biotherapeutics
Related Articles
Eczema
The 7 Types of Eczema: A Dermatologist's Complete Guide to Identifying and Treating Each
Feb 10, 2026 · 8 min read

Psoriasis
When Weight Is Part of the Psoriasis Story: The Conversation That Often Gets Missed
May 18, 2026 · 10 min read
Psoriasis
GLP-1 for Psoriasis: How Weight Loss Can Improve Skin Clearance
May 17, 2026 · 13 min read